

Abstract
Objective: Individuals with bipolar II disorder (BD-II) and depression face limited treatment options and are often excluded from psilocybin therapy trials due to concerns about precipitating mania or psychosis. The objective of this study was to evaluate the safety, tolerability, and preliminary efficacy of psilocybin therapy in individuals with BD-II and depression.
Methods: We conducted an open-label, single-arm pilot trial from 2022–2025 in which 14 participants with BD-II depression, diagnosed using adapted criteria requiring ≥2 consecutive days of hypomanic symptoms, received 10 mg of psilocybin, followed by 25 mg if symptoms persisted. Participants completed psychotherapy before, during, and after psilocybin sessions and were proactively monitored for adverse events. Depression and quality of life were assessed using the Montgomery-Asberg Depression Rating Scale (MADRS; primary end point 21 days after each participant’s final administration session) and the Quality of Life in Bipolar Disorder Questionnaire (QoL-BD), alongside exploratory measures.
Results: Psilocybin was well tolerated, with only transient increases in heart rate and blood pressure and no serious adverse events. Common side effects included mild-to-moderate anxiety, nausea, and headache. Three participants experienced notable psychiatric events (suicidal ideation or hypomania), which resolved with support. Following the 10 mg session, MADRS scores improved significantly (−12.7 [2.7], P<.001), with 4 participants (28.5%) meeting remission criteria and therefore not proceeding to the 25 mg session; 9 participants received the 25 mg dose. Among those who received the 25 mg dose, MADRS scores improved significantly 21 days following 25 mg (−18.6 [3.1], P<.001). QoL-BD scores also improved at 90 days following the final dose (31.2 [10.2], P=.004).
Conclusion: These findings suggest that psilocybin therapy may be safe, tolerable, and preliminarily efficacious for treating depression in BD-II, but randomized controlled trials are needed to confirm efficacy and optimize protocols.
Trial Registration: ClinicalTrials.gov identifier: NCT05065294
J Clin Psychiatry 2026;87(4):25m16227
Author affiliations are listed at the end of this article.
From the Editors

Are you a healthcare provider?
Add your NPI to personalize your JCP experience.
Bipolar II disorder (BD-II) is a chronic, debilitating illness affecting ∼0.4% to 1% of the global population, characterized by recurrent depressive episodes, limited treatment options, and high rates of comorbid anxiety, posttraumatic stress disorder (PTSD), personality disorders, attachment insecurity, and suicidality.1–3 Psilocybin has shown promising antidepressant effects across disorders4–7 when administered alongside psychotherapy, often referred to as psilocybin-assisted therapy or psilocybin therapy. Despite urgent clinical need, individuals with personal or even a family history of BD have been largely excluded from psilocybin trials because of theoretical concerns about mania risk and case reports of adverse outcomes,8–10 though the basis for excluding individuals with only a family history has been questioned.8 In 3 small open-label studies (total N=23) of psilocybin therapy for BD-II depression, no serious adverse events were reported and preliminary antidepressant effects were observed, though heterogeneity in dosing, inclusion criteria, and adverse event reporting limits interpretation.11–13
Despite psilocybin’s promise, critical challenges remain in translating early findings to clinical practice. Adverse event reporting has been inconsistent, often emphasizing acute drug-related effects while neglecting adverse events occurring across the duration of the study, underscoring the need for more systematic and comprehensive capture of all adverse events in trials of psychedelic therapy.14,15 Restrictive eligibility criteria, particularly the exclusion of participants with psychiatric comorbidities, further limit generalizability.16 To address these gaps, we conducted an open-label, dose-escalation pilot study to evaluate psilocybin therapy’s safety, tolerability, and preliminary efficacy in BD-II depression, emphasizing systematic adverse event capture and real-world psychiatric complexity.
METHODS
Participants
We enrolled adults aged 18–70 years with BD-II experiencing a current major depressive episode >4 weeks in duration and at least moderate severity (Montgomery-Asberg Depression Rating Scale [MADRS] >18).17 All had ≥1 prior unsuccessful medication trial for BD-II lasting ≥6 weeks. Exclusion criteria included serious cardiovascular, neurological, or other medical illness; current hypomania; history of psychotic disorder; moderate or greater substance use disorder in the past 12 months; psychedelic use within 6 months; and score of 4 or greater (active suicidal ideation with some intent to act without specific plan) on the Columbia-Suicide Severity Rating Scale (C-SSRS) at baseline. Four participants on medications with potential psilocybin interactions tapered off to ensure clearance (≥5 half-lives) before each administration. For safety, each participant designated a support person who saw the participant in person at least 5 days per week and monitored behavior and assisted with transport after sessions.
Study Design and Procedures
Participants were recruited from ClinicalTrials.gov, clinician referral, and self-referral and were screened for eligibility using serum laboratory evaluation, electrocardiogram, physical examination, vital signs, detailed medical history, and the Structured Clinical Interview for DSM-5 (SCID-5).18 To diagnose BD-II, we employed an adapted criterion of ≥2 consecutive days of hypomanic symptoms (instead of 4), based on evidence supporting greater clinical utility of this threshold.19 Additional assessments included the MADRS and C-SSRS.20
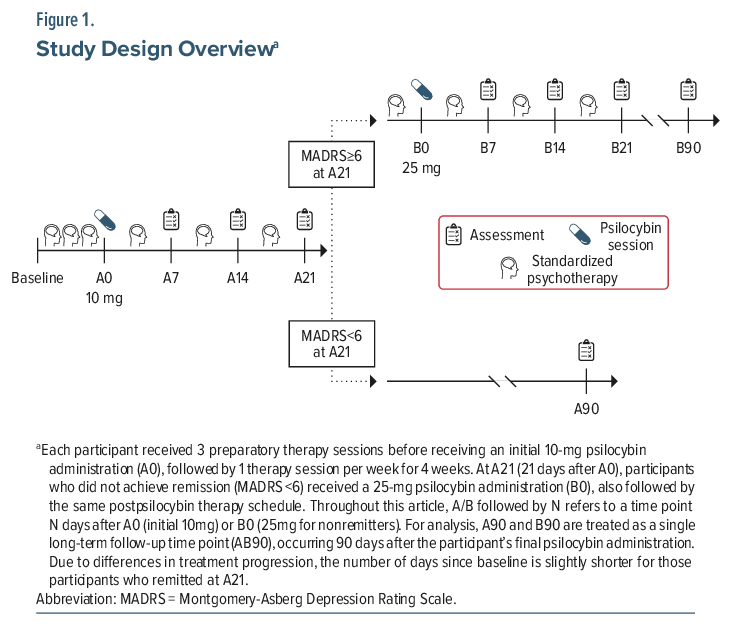
Following eligibility determination and baseline assessments, each participant was paired with a licensed marriage and family therapist with master’s level training for psychotherapy sessions (see Supplementary Methods, description of the psychotherapeutic component of the trial for details) before, during, and following 1 to 2 psilocybin administration sessions. During administration sessions, participants received oral synthetic psilocybin (3-[2-(dimethylamino)ethyl]-1H-indol-4-yl] dihydrogen phosphate), provided by the Usona Institute. Given theoretical risks of inducing mania in BD-II, a cautious dose-escalation protocol was employed. Participants first received 10 mg of psilocybin, and, if that was well tolerated and depressive symptoms persisted (MADRS ≥7) at day 21, they were eligible for a second administration of 25 mg—the standard dose in modern trials. This approach minimized the risk of administering high-dose psilocybin to participants who were no longer depressed. To reduce demand characteristics, participants were not informed of the specific MADRS threshold used to determine eligibility for the second session. Instead, participants were told that the decision to proceed was determined based on safety and other outcomes. Participants completing 1 psilocybin session received >14 hours of psychotherapy; those completing 2 sessions received >27 hours (Figure 1).
Both 10 mg and 25 mg sessions followed an identical standardized protocol in a comfortable, living-room–like setting (see Supplementary Methods, psilocybin administration session environment). Vital signs and urine drug screens were conducted to confirm safety for psilocybin administration. The participant’s therapist was joined by an assisting therapist (licensed or working toward licensure) to provide continuous safety monitoring and psychological support during the acute effects of psilocybin. Rescue medications were available for emergent situations at the discretion of the on-site medical provider.
All procedures involving human subjects were approved by the US Food and Drug Administration, the US Drug Enforcement Agency, the Regulatory Approval Committee of California, and the University of California San Francisco Institutional Review Board. We describe minor deviations from the registered study protocol in Supplementary Methods.
Measures
Participants completed structured assessments 7, 14, and 21 days after the 10 mg session (A7, A14, A21) and, if they received a second session, after the 25 mg session (B7, B14, B21). Selected assessments were repeated 90 days after the final session (AB90). Participants who remitted after the 10 mg session reached AB90 earlier than nonremitters who proceeded to the 25 mg session.
Safety and Tolerability
The primary objective was to assess psilocybin therapy’s safety and tolerability. Safety was assessed by vital signs, adverse event reporting, suicidality, and symptoms of mania or psychosis. Adverse events were systematically recorded at baseline and each visit; any new or changed symptom from baseline was documented regardless of severity or attribution. During administration sessions, adverse events were also captured through vital sign monitoring, therapist observation, and participant self-report. Suicidality was assessed with the C-SSRS,20 including its Ideation Severity subscale. The Young Mania Rating Scale (YMRS)21 and Positive and Negative Syndrome Scale (PANSS)22 assessed treatment-emergent (hypo)mania and psychosis.
Treatment tolerability was measured by classifying adverse events using standard regulatory definitions, with severity denoting symptom intensity and seriousness determined by outcome-based criteria (eg, death, life-threatening event, or inpatient hospitalization); recommendations for emergency evaluation alone did not constitute a serious adverse event in the absence of these criteria. Further, the Insomnia Severity Index (ISI)23 assessed treatment-emergent insomnia. Finally, acceptability was evaluated at AB90 with a 5-item study-developed Treatment Satisfaction Questionnaire (TSQ; available on request from the corresponding author).
Preliminary Efficacy
The primary efficacy end point was change in MADRS scores from baseline to 21 days after each participant’s final administration session (A21/B21). The Quality of Life in Bipolar Disorder Questionnaire (QoL-BD),24 a secondary outcome, was administered at A21, B21, and AB90.
Exploratory Measures
Positive and negative treatment expectations were assessed with the Stanford Expectations of Treatment Scale (SETS),25 PTSD symptoms with the PTSD Checklist for DSM-5 (PCL-5),26 attachment style with the anxious and avoidance subscales of the Experiences in Close Relationships Scale (ECR-M16),27 and early life trauma with the Adverse Childhood Experiences (ACE) Questionnaire.28
To characterize psychedelic experiences, participants completed the Emotional Breakthrough Inventory (EBI),29 Mystical Experience Questionnaire (MEQ),30 and Challenging Experience Questionnaire (CEQ)31 after each administration session. These scales assess, respectively, emotional insight or resolution, mystical-type experiences (eg, unity, transcendence, ineffability), and difficult or distressing experiences (eg, fear, grief, isolation). The schedule of study activities and additional exploratory measures are provided in Supplementary Methods.
Statistical Analysis
To assess change in outcome scores from baseline, we used mixed effects linear models with score as dependent variable, time point as fixed effect, and patient ID as random effect. All models were constructed in R (v4.1.2) using the lme4 (v1.1-27.1) and lmerTest (v3.1-3) packages. Normality of residuals was checked from QQ plots, and homeoskedasticity was assessed with scale-location plots. While no major violation of assumptions was observed, normality could not be confirmed due to the small sample size. To mitigate this concern, paired Wilcoxon signed-rank tests were also implemented and yielded the same overall pattern of results as the mixed-effects models. Missing data were not imputed, and unadjusted P values are disclosed. However, given the large number of secondary measures and the lack of a predefined statistical analysis plan, we present the false discovery rate (FDR with a family-wise error rate of 0.05) adjusted P values for all statistical comparisons in Supplementary Table 1 (results of mixed effect models) and Supplementary Table 2 (results of Wilcoxon tests).
To assess associations between baseline characteristics or acute psilocybin experience measures and treatment efficacy, we used Spearman correlations, supplemented by Pearson and Kendall correlations to evaluate robustness.
Phenomenological characteristics of the psychedelic experience, as quantified by the MEQ, EBI, and CEQ, were compared between 10 mg and 25 mg sessions using paired t tests.
All baseline variables are presented as means (standard deviations) in Supplementary Table 3. For analyses evaluating change from baseline, results are reported as estimated mean differences (standard errors) unless otherwise specified.
Analysis scripts are available on the project’s GitHub repository.
RESULTS
Sample
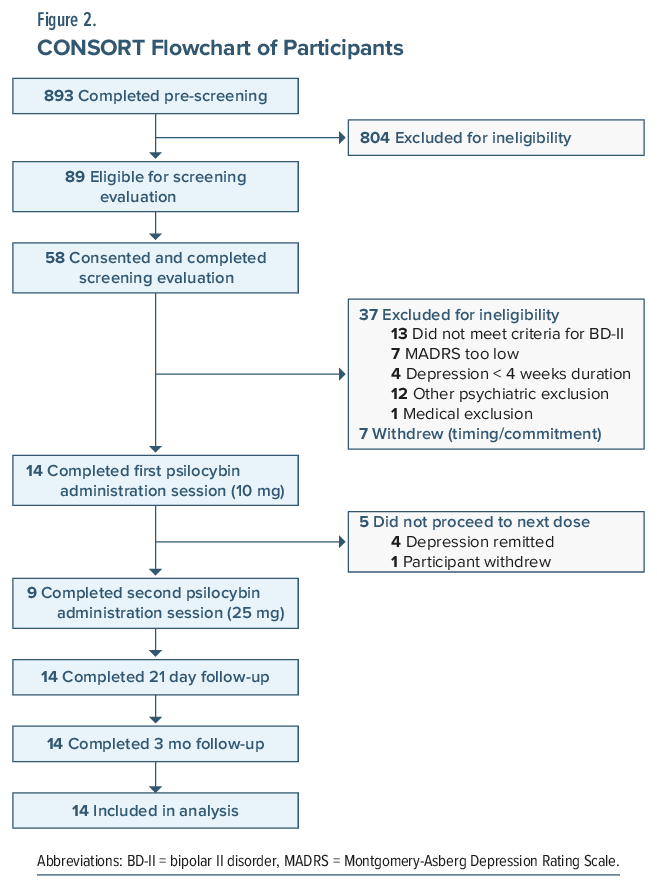
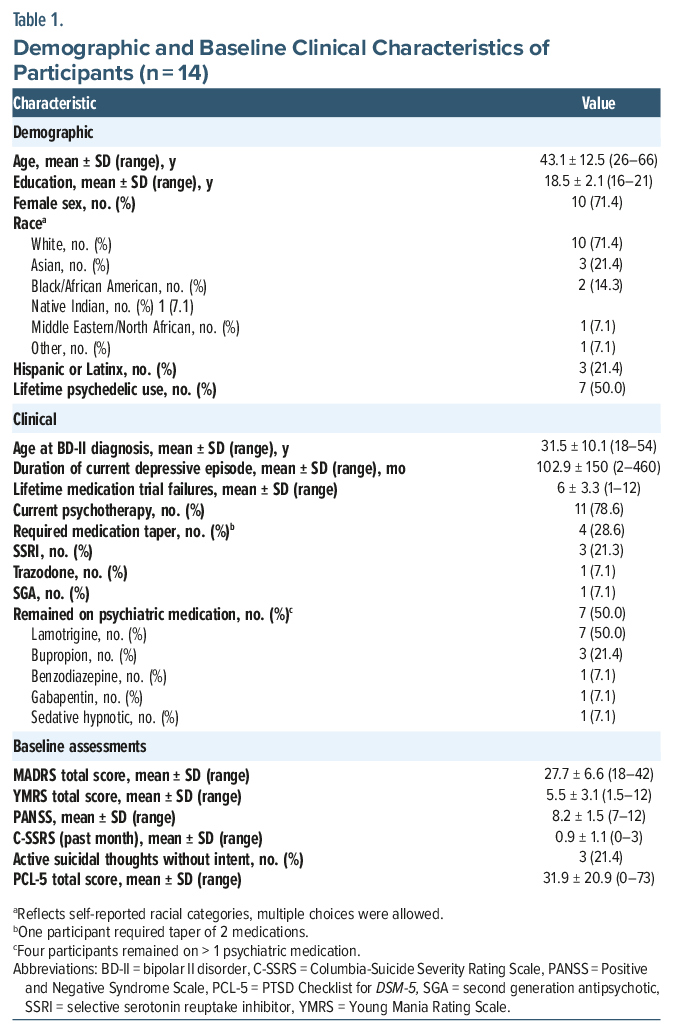
Of 893 participants who completed prescreening, 58 provided written consent, and 14, with an average baseline MADRS of 27.7 (6.6), received psilocybin at least once and were included in analysis; see Figure 2 and Table 1. All 14 completed the 21-day assessment after their 10 mg session; all 9 who received 25 mg also completed the 21-day postsession assessment (100% retention).
Safety
As expected, psilocybin produced transient increases in heart rate and blood pressure. Mean peak heart rate was 84.8 (17.0) bpm after 10 mg and 84.4 (17.3) bpm after 25 mg. Peak systolic/diastolic pressures averaged 141.6 (15.5)/86.3 (8.9) mm Hg for 10 mg and 144.7 (18.3)/88.9 (8.3) mm Hg for 25 mg, see Supplementary Figure 1 for details.
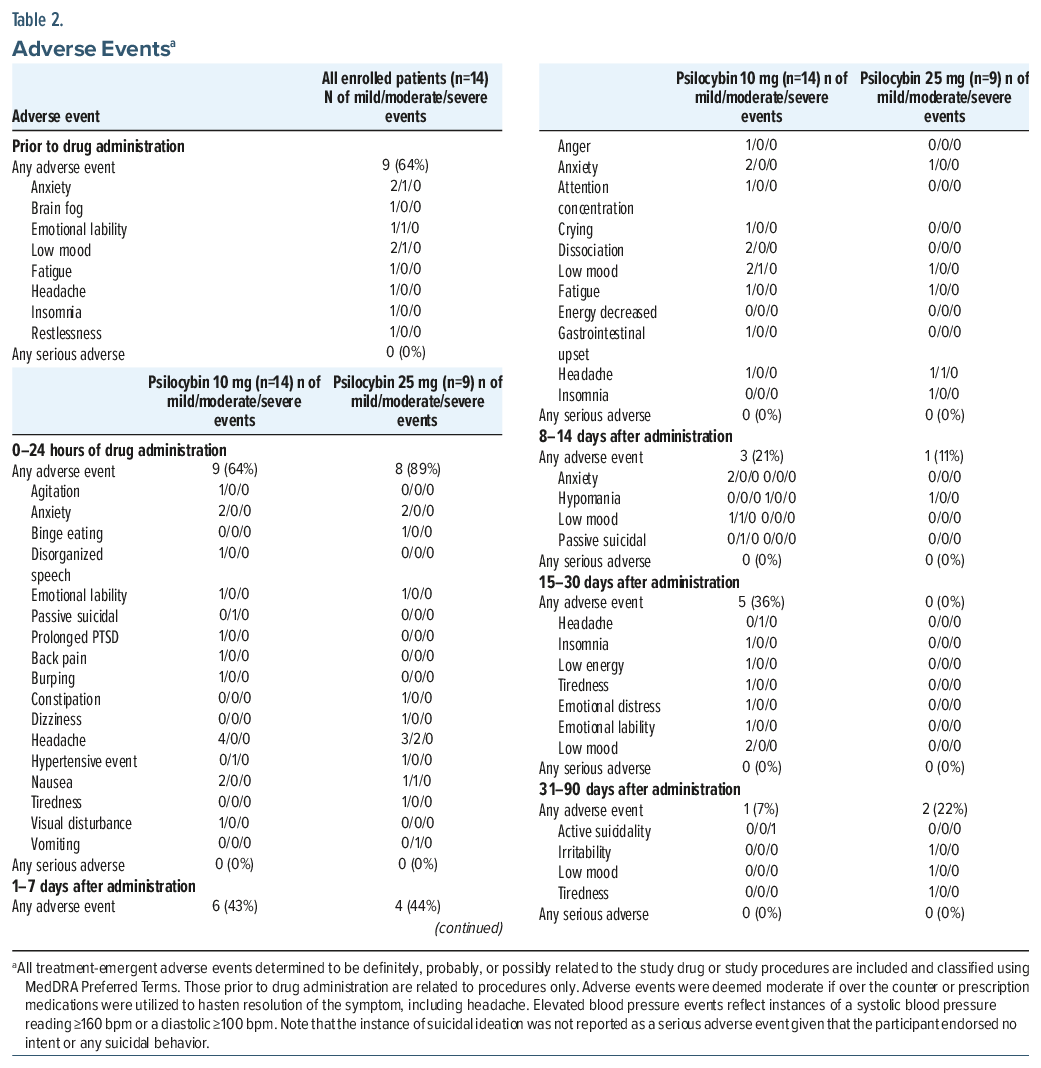
Suicidal ideation was low at baseline and across postadministration time points, with 10 of 14 participants maintaining scores ≤1 on the C-SSRS throughout the study. No participants reported a higher C-SSRS Ideation Severity subscale score at 21 days (A21/B21) following their final administration session compared to baseline. There was a statistically, but not clinically, significant decrease on this subscale score (average reduction of ∼0.7 points) at every postadministration time point. However, the 1 severe AE (worsening suicidal ideation with intent but no plan) occurred 37 days following a challenging psychological experience during their 10 mg session. The participant decided not to move forward with the 25 mg session despite not reaching depression remission criteria. Study physicians offered additional psychological support and ultimately recommended emergency services for worsening suicidal ideation. The participant declined emergency services, did not engage in suicidal behavior, and instead accessed mental health resources external to the trial the following day with subsequent resolution of suicidal ideation. One additional participant experienced suicidal ideation 11 days after their 10 mg session. This was attributed to both external life stressors and insights that emerged during the psilocybin experience. The ideation resolved in 2 days with support from study therapists.
Mean scores on the YMRS and PANSS did not significantly worsen. However, 1 participant experienced significantly increased YMRS scores concerning for hypomania 14 days following their 25 mg session. This participant had tapered off trazodone (75 mg nightly) over 4 weeks prior to dosing. Symptoms consisted of mildly elevated mood, increased energy, and reduced sleep (approximately 5 hours per night) lasting nearly 3 days, were less severe and shorter in duration than the participant’s prior hypomanic episodes, and resolved without pharmacologic intervention. Symptoms did not progress to mania, and the YMRS returned to participant’s baseline level by B21. No additional psychological support or emergency services were utilized. See Supplementary Figure 2 for the individual scores of selected safety related measures over the course of the treatment (YMRS, PANSS, C-SSRS, and Clinical Global Impression–Improvement).
Another participant experienced significant emotional distress on hearing they would not progress to the second psilocybin administration session because their MADRS score indicated remission at A21. Study physicians communicated with the participant to ensure adequate follow-up care was established. See Table 2 for list of adverse events.
Tolerability and Acceptability
The majority of adverse events occurred within 24 hours of psilocybin administration, most commonly mild-moderate anxiety, nausea, and/or headache. No medications were required to mitigate adverse effects during administration sessions. Of the 143 total adverse events, 83% of events were mild, 15% were moderate, and a single event was severe. No serious adverse events were observed.
ISI scores improved from baseline to every time point after the 10 mg and 25 mg sessions (A21: −5 [1.4], P<.001; B21: −7.0 [1.6], P<.001), including at AB90 (−3.1 [1.4], P=.036); Hedges g=1.0. Eight of the eleven (73%) participants who completed the TSQ would recommend the treatment; see Supplementary Figure 3 for details.
Preliminary Efficacy
Relative to baseline, MADRS scores significantly improved at all time points (A21: −12.7 [2.7], n=14, P<.001; B21: −19.2 [3.0], n=9, P <.001; see Supplementary Table 1 for results at other time points), with 4 participants (28.5%) meeting remission criteria (MADRS ≤6) at A21 and therefore not proceeding to the 25 mg session per protocol (see Figure 3). At B21, 3 out of 9 patients met remission criteria (33%). Using the more traditional definition of MADRS≤10 for remission, the remission rates were 36% and 56% at A21 and B21, respectively. The MADRS response rates (≥50% improvement relative to baseline) were also 36% and 56% at A21 and B21, respectively.
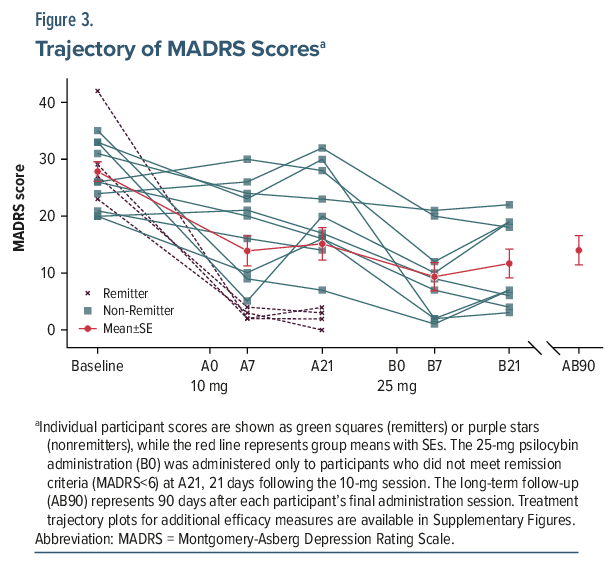
After the 25 mg session, MADRS scores improved from baseline (B21: −18.6 [3.1], n = 9, P < .001). Sustained improvements in MADRS scores were observed at the 90-day assessment compared to baseline (AB90: −14.3 [2.8], n = 12, P < .001); Hedges g = 1.9.
QoL-BD scores improved 21 days following the 10 and 25 mg administration sessions (A21: 35.5 [9.4], P<.001; B21: 55.9 [10.9], P<.001) and at the 90-day assessment (AB90: 31.2 [10.2], P=.004); Hedges g=1.6. See Supplementary Figure 4 for the change of group averages on QoL-BD and selected other measures (ISI, Quick Inventory of Depressive Symptomatology, and Mood Disorder Burden Interview).
Exploratory Analysis
On the SETS (0=strongly disagree, 6=strongly agree), mean scores were 2.0 (1.4) for positive and 4.4 (1.8) for negative expectancy items, indicating generally low treatment optimism and elevated concerns at baseline; see Supplementary Figure 5 for details.
At baseline, 10 of 14 participants reported PCL-5 events likely meeting DSM-5 Criterion A for PTSD26; 2 others described possibly qualifying events; we included PCL-5 scores from all 12 of these participants in our analyses. At baseline, mean PCL-5 scores were 31.9 (20.9), meeting a National Center for PTSD threshold for clinically significant PTSD (≥31).32 PCL-5 scores decreased at the 90-day assessment (AB90: −13.9 [6.1]; P=.048, Hedges g=−0.87), which was the only additional time point that included the PCL-5.
MEQ and CEQ scores were numerically but not significantly lower after 10 mg than 25 mg. Normalized scores (0=minimum, 1=maximum possible): MEQ: 0.53 (0.28) vs 0.63 (0.29); CEQ: 0.20 (0.13) vs 0.30 (0.19). EBI scores were similar across sessions: 0.78 (0.14) vs. 0.76 (0.18).
At baseline, participants showed moderate-to-elevated attachment insecurity on the ECR-M16, with mean item scores of 4.0 (1.2) for anxiety and 3.9 (1.8) for avoidance subscales—both at the upper end of values reported in prior clinical and nonclinical samples (∼3.1–3.8 and ∼2.8–3.8, respectively).33 Scores on both scales decreased at A21 and B21 time points (anxiety: A21: −5.9 [2.4]; P=.019; B21: −7.3 [2.8]; P=.014; avoidance: A21: −6.6 [2.5]; P= .011; B21: −7.7 [2.9]; P=.012). At the AB90 assessment, avoidance remained (−5.9 [2.6]; P=.032), with a nonsignificant trend toward reduced anxiety (−4.8 [2.5]; P=.067).
We found no robust associations between baseline measures (ACE, SETS, and PCL-5) or measures related to the acute drug experience (EBI/MEQ/CEQ) and any clinical outcome, see Supplementary Figure 6 for correlation matrices. Equivalence could not be established between expectancy and any clinical outcome, meaning the data are inconclusive on expectancy effects, see Supplementary materials for details.
Analysis of additional secondary outcomes (YMRS, PANSS, Quick Inventory of Depressive Symptomatology, Bipolar Recovery Questionnaire Mood Disorder Burden Interview and Transformational Experiences Questionnaire) can be found in Supplementary Methods, along with full statistical outputs (Supplementary Tables 1 and 2).
DISCUSSION
This open-label, dose-escalation trial evaluated the safety and tolerability of psilocybin therapy in individuals with moderate-to-severe BD-II depression, most of whom had significant PTSD symptoms and attachment insecurity. No cases of acute mania or psychosis were observed, though 1 participant experienced hypomania. Prior to psilocybin administration, nearly two-thirds of participants experienced a mild adverse event possibly related to trial procedures and most reported at least 1 event during the trial, most commonly headache, nausea, or anxiety during administration. Although a small number of participants experienced psychiatric symptom exacerbations, overall rates and distributions of adverse events were consistent with other psilocybin trials.4,6 Depression symptoms (MADRS), the primary, albeit preliminary, clinical outcome, and quality of life (QoL-BD) both showed large and sustained improvements over the 90-day follow-up period. These findings are consistent with other psilocybin trials in unipolar4–7 and BD-II11–13 depression. Our results provide preliminary evidence that psilocybin therapy may benefit BD-II depression with a safety profile comparable to other populations.
Three participants experienced concerning exacerbations of psychiatric symptoms—active suicidal ideation 37 days, passive suicidal ideation 11 days, and a hypomanic episode 14 days after psilocybin administration. The relationship of these events to psilocybin remains unclear given the clinical complexity of the sample, recent medication tapers, and the cyclical nature of BD-II. In a large trial of psilocybin therapy for treatment-resistant depression, worsened suicidality occurred in 15.2–16.0% of participants across dosage groups through week 12,6 underscoring the need for ongoing monitoring for suicidality in the weeks to months following administration.
Although participants were informed they would receive 1 or 2 psilocybin administrations, the use of a prespecified remission threshold to determine eligibility for the second session was not disclosed, to minimize demand characteristics. While this approach prioritized safety, participants experienced disappointment or confusion when they were not offered a second administration session, feeling abruptly disconnected from a potentially beneficial intervention. Future designs may benefit from more flexible, transparent decision-making processes that balance safety, demand characteristics, and participant engagement.
Our study population had clinically significant PTSD symptoms and moderate-to-elevated attachment insecurity at baseline. Given the promising results of 3,4-methylenedioxymethamphetamine (MDMA)-assisted psychotherapy for PTSD, few trials have investigated classic psychedelics for this indication—potentially reflecting the widespread perception that PTSD was already being addressed through MDMA-focused efforts.34 A recent pilot study by McGowan et al demonstrated clinically meaningful and sustained reductions in clinician- and self-reported PTSD symptoms following psilocybin therapy in individuals with PTSD.35 In our trial, psilocybin therapy was associated with sustained reductions in self-reported PTSD symptoms and attachment-related anxiety and avoidance. These effects mirror those observed in our earlier study of long-term AIDS survivors, where a single administration also improved both domains.36 Notably, neither intervention specifically targeted PTSD or attachment—two domains that are typically resistant to treatment.37,38 Together, these results suggest that psilocybin therapy may hold promise for addressing trauma-related and attachment-based psychopathology.
In our study, 4 participants experienced remission of depression after a 10 mg dose of psilocybin, suggesting that some individuals with BD-II may achieve remission of depression following this lower dose, potentially reducing the need for higher doses and associated risks. We note that in treatment-resistant depression, a recent trial found no statistically significant changes in depression 3 weeks after 10 mg psilocybin treatment relative to a 1mg control condition.6 Thus, more work is required to investigate the potentially efficacy of the 10 mg dose. Participants reported subjective experiences on the MEQ, EBI, and CEQ following 10 mg that were similar to those observed after 25 mg—both within this trial and in a prior study of psilocybin for unipolar depression,4 see Supplementary Figure 7 and Supplementary Table 4 for details. These relatively intense experiences may have contributed to therapeutic improvement, offering a possible explanation for the clinical effects observed at this lower dose. However, it is also possible that some or all of the observed remissions after the 10 mg session reflect placebo responses.
We acknowledge several limitations. First, the small sample size and open-label design warrant cautious interpretation. The placebo response likely explains some of the observed benefits. However, while critiques of psilocybin therapy often highlight expectancy biases associated with the favorable media coverage of the treatment,16 our participants’ baseline expectancy was generally negative and was not associated with clinical outcomes, see Supplementary Figure 6 for details. This lack of relationship between self-reported expectancies and outcomes is consistent with the only other psilocybin trial that measured expectancy.39 Second, our exclusion criteria reduce generalizability to more complex psychiatric presentations and to those with BD-I. Third, most concomitant psychotropic medications were exclusionary, further reducing the generalizability of our findings. Psilocin, the active metabolite of psilocybin, acts via serotonergic pathways. To mitigate the risk of treatment-emergent mania, concurrent serotonergic agents such as SSRIs were tapered prior to psilocybin administration.40 However, emerging safety data support cautious coadministration with serotonergic antidepressants41 which future trials may explore with appropriate safeguards. Sociodemographic characteristics, including sex differences, represent an important consideration in clinical trials of psychedelic therapy.42 The present open-label pilot study was not powered to evaluate these differences, and analyses were not performed to avoid overinterpretation. Future, adequately powered trials should explicitly examine the effects of these variables on the intervention.
In summary, results of this open-label, dose escalation study suggest that psilocybin therapy may be a safe, tolerable, and possibly efficacious treatment for BD-II depression. Randomized, placebo-controlled trials are warranted to examine efficacy in larger samples with common psychiatric comorbidities observed with BD-II. Dose-response studies are important to further optimize efficacy while mitigating psychological and physiologic risks, particularly considering our observed 4 remissions following the 10 mg dose. We join others in calling for transparent, complete, and standardized characterization of adverse events in psychedelic clinical trials.14
Article Information
Published Online: September 21, 2026. https://doi.org/10.4088/JCP.25m16227
© 2026 Physicians Postgraduate Press, Inc.
Submitted: November 13, 2025; accepted May 20, 2026.
To Cite: Downey AE, Szigeti B, Bradley ER, et al. An open-label, dose-escalation trial of psilocybin-assisted therapy for bipolar II depression. J Clin Psychiatry 2026;87(4):25m16227.
Author Affiliations: Translational Psychedelic Research Program, Department of Psychiatry and Behavioral Sciences, Weill Institute for Neurosciences, University of California, San Francisco (Downey, Szigeti, Bradley, Fernandes-Osterhold, Sakai, Llerena, Fredenburg, Nerayo, Evans-Riera, Nielsen, O’Donovan, Woolley); Department of Pediatrics, University of California, San Francisco (Downey); Centre for Psychedelic Research, Imperial College London, United Kingdom (Szigeti); Parkinson’s Disease Research, Education, and Clinical Center, San Francisco Veterans Affairs Medical Center, San Francisco, California (Bradley); San Francisco Veterans Affairs Medical Center, San Francisco, California (Bradley, O’Donovan, Woolley); Department of Psychology, San Francisco State University, San Francisco, California (Gard); Department of Psychiatry and Behavioral Sciences, Weill Institute for Neurosciences, University of California, San Francisco (Krystal).
Drs Downey and Szigeti are co-first authors.
Corresponding Author: Josh D. Woolley, MD, PhD, 675 18th St, #001, San Francisco, CA 94107 ([email protected]).
Author Contributions: All authors approved the final version of the manuscript and agree to be accountable for the work. Drs Downey and Szigeti contributed equally to this work.
Relevant Financial Relationships: Dr Woolley reports being a paid consultant for Magdalena Biosciences, Arcadia Medicine, and MindMed and serves as a Department of Justice expert witness. The other authors have no conflicts of interest to disclose.
Funding/Support: This study was supported by a philanthropic gift from an anonymous donor without medical industry affiliation. Dr Downey is supported by the National Center for Advancing Translational Sciences of the National Institutes of Health under Award Number KL2TR001870.
Role of the Sponsor: The sponsor had no involvement in the study design, data collection, analysis, interpretation, or manuscript preparation.
Ethical Standards: The authors assert that all procedures contributing to this work comply with the ethical standards of the relevant national and institutional committees on human experimentation and with the Helsinki Declaration of 1975, as revised in 2008.
Transparency Declaration: Drs Downey, Szigeti, and Woolley affirm that the manuscript is an honest, accurate, and transparent account of the study being reported; that no important aspects of the study have been omitted; and that any discrepancies from the study as planned (and, if relevant, registered) have been explained.
Data Availability Statement: Code can be accessed on the project’s GitHub page (https://github.com/UCSF-Psychiatry-TrPR-Program/BAP1); data are available upon request by qualified researchers.
ORCID: Amanda E. Downey: https://orcid.org/0000-0002-5206-7798; Balazs Szigeti: https://orcid.org/0000-0003-3809-6442; Ellen Bradley: https://orcid.org/0000-0001-6787-1490; Gisele Fernandes: https://orcid.org/0009-0004-6712-6000; Kimberly Sakai: https://orcid.org/0009-0006-9991-6757; Katiah Llerena: https://orcid.org/0000-0002-9769-172X; Andrew Krystal: https://orcid.org/0000-0002-6702-781X; Aoife O’Donovan: https://orcid.org/0000-0003-2353-7217; David E. Gard: https://orcid.org/0000-0002-0446-4000; Josh Woolley: https://orcid.org/0000-0002-4378-0014
Supplementary Material: Available at Psychiatrist.com.
Clinical Points
- Individuals with bipolar II disorder have been excluded from psychedelic therapy trials due to safety concerns, leaving a critical evidence gap regarding the risks and benefits of this intervention in this population.
- These study findings suggest that with psychological support and longitudinal safety monitoring, psilocybin therapy may warrant further study as a potential treatment option for those with bipolar II disorder and depression.
References (42)

- Grande I, Berk M, Birmaher B, et al. Bipolar disorder. Lancet. 2016;387(10027):1561–1572. PubMed CrossRef
- Karanti A, Kardell M, Joas E, et al. Characteristics of bipolar I and II disorder: a study of 8766 individuals. Bipolar Disord. 2020;22(4):392–400. PubMed CrossRef
- Swartz HA, Suppes T. Bipolar II disorder: understudied and underdiagnosed. Focus (Am Psychiatr Publ). 2023;21(4):354–362. PubMed CrossRef
- Carhart-Harris R, Giribaldi B, Watts R, et al. Trial of psilocybin versus escitalopram for depression. N Engl J Med. 2021;384(15):1402–1411. PubMed CrossRef
- Carhart-Harris RL, Bolstridge M, Rucker J, et al. Psilocybin with psychological support for treatment-resistant depression: an open-label feasibility study. Lancet Psychiatry. 2016;3(7):619–627. PubMed CrossRef
- Goodwin GM, Aaronson ST, Alvarez O, et al. Single-dose psilocybin for a treatment-resistant episode of major depression. New Engl J Med. 2022;387(18):1637–1648. PubMed CrossRef
- Raison CL, Sanacora G, Woolley J, et al. Single-dose psilocybin treatment for major depressive disorder: a randomized clinical trial. JAMA. 2023;330(9):843–853. PubMed CrossRef
- Downey AE, Bradley ER, Lerche AS, et al. A plea for nuance: should people with a family history of bipolar disorder be excluded from clinical trials of psilocybin therapy?. Psychedelic Med (New Rochelle). 2024;2(2):61–73. PubMed CrossRef
- Gard DE, Pleet MM, Bradley ER, et al. Evaluating the risk of psilocybin for the treatment of bipolar depression: a review of the research literature and published case studies. J Affect Disord Rep. 2021;6:100240. CrossRef
- Morton E, Sakai K, Ashtari A, et al. Risks and benefits of psilocybin use in people with bipolar disorder: an international web-based survey on experiences of “magic mushroom” consumption. J Psychopharmacol. 2023;37(1):49–60. PubMed CrossRef
- Aaronson ST, van der Vaart A, Miller T, et al. Single-dose synthetic psilocybin with psychotherapy for treatment-resistant bipolar type II major depressive episodes: a nonrandomized open-label trial. JAMA Psychiatry. 2024;81(6):555–562. PubMed CrossRef
- Meshkat S, Kaczmarek E, Doyle Z, et al. Psilocybin-assisted psychotherapy for treatment-resistant depression in bipolar II disorder. Psychedelic Med (New Rochelle). 2025;3(1):53–58. PubMed CrossRef
- Rosenblat JD, Meshkat S, Doyle Z, et al. Psilocybin-assisted psychotherapy for treatment resistant depression: a randomized clinical trial evaluating repeated doses of psilocybin. Med. 2024;5(3):190–200.e5. PubMed CrossRef
- Hinkle JT, Graziosi M, Nayak SM, et al. Adverse events in studies of classic psychedelics: a systematic review and meta-analysis. JAMA Psychiatry. 2024;81(12):1225–1235. PubMed CrossRef
- Vaughan B, Goldstein MH, Alikakos M, et al. Frequency of reporting of adverse events in randomized controlled trials of psychotherapy vs. psychopharmacotherapy. Compr Psychiatry. 2014;55(4):849–855. PubMed CrossRef
- Van Elk M, Fried EI. History repeating: a roadmap to address common problems in psychedelic science. PsyArXiv. 2023. doi:10.31234/osf.io/ak6gx. CrossRef
- Montgomery SA, Asberg M. A new depression scale designed to be sensitive to change. Br J Psychiatry. 1979;134:382–389. PubMed CrossRef
- First MB. Structured Clinical Interview for the DSM (SCID). In: The Encyclopedia of Clinical Psychology. John Wiley & Sons, Ltd; 2015:1–6.
- Suppes T, Dennehy EB, Gibbons EW. The longitudinal course of bipolar disorder. J Clin Psychiatry. 2000;61(Suppl 9):23–30. PubMed
- Posner K, Brown GK, Stanley B, et al. The Columbia-Suicide Severity Rating Scale: initial validity and internal consistency findings from three multisite studies with adolescents and adults. Am J Psychiatry. 2011;168(12):1266–1277. PubMed CrossRef
- Mohammadi Z, Pourshahbaz A, Poshtmashhadi M, et al. Psychometric properties of the Young Mania Rating Scale as a mania severity measure in patients with bipolar I disorder. J Pract Clin Psychol. 2018;6(3):175–182.
- Kay SR, Opler LA, Lindenmayer JP. The Positive and Negative Syndrome Scale (PANSS): rationale and standardisation. Br J Psychiatry. 1989;155(S7):59–65. PubMed
- Morin CM, Belleville G, Bélanger L, et al. The Insomnia Severity Index: psychometric indicators to detect insomnia cases and evaluate treatment response. Sleep. 2011;34(5):601–608. PubMed CrossRef
- Morton E, Murray G, Yatham LN, et al. The Quality of Life in Bipolar Disorder (QoL.BD) questionnaire a decade on – a systematic review of the measurement of condition-specific aspects of quality of life in bipolar-disorder. J Affect Disord. 2021;278:33–45. PubMed CrossRef
- Younger J, Gandhi V, Hubbard E, et al. Development of the Stanford Expectations of Treatment Scale (SETS): a tool for measuring patient outcome expectancy in clinical trials. Clin Trials. 2012;9(6):767–776. PubMed CrossRef
- Blevins CA, Weathers FW, Davis MT, et al. The Posttraumatic Stress Disorder Checklist for DSM-5 (PCL-5): development and initial psychometric evaluation. J Trauma Stress. 2015;28(6):489–498. PubMed CrossRef
- Fraley RC, Waller NG, Brennan KA. An item response theory analysis of self-report measures of adult attachment. J Personality Soc Psychol. 2000;78(2):350–365. PubMed CrossRef
- Murphy A, Steele M, Dube SR, et al. Adverse Childhood Experiences (ACEs) questionnaire and Adult Attachment Interview (AAI): implications for parent child relationships. Child Abuse Negl. 2014;38(2):224–233. PubMed CrossRef
- Roseman L, Haijen E, Idialu-Ikato K, et al. Emotional breakthrough and psychedelics: validation of the Emotional Breakthrough Inventory. J Psychopharmacol. 2019;33(9):1076–1087. PubMed CrossRef
- Barrett FS, Johnson MW, Griffiths RR. Validation of the revised Mystical Experience Questionnaire in experimental sessions with psilocybin. J Psychopharmacol. 2015;29(11):1182–1190. PubMed CrossRef
- Barrett FS, Bradstreet MP, Leoutsakos JMS, et al. The Challenging Experience Questionnaire: characterization of challenging experiences with psilocybin mushrooms. J Psychopharmacol. 2016;30(12):1279–1295. PubMed CrossRef
- Bovin MJ, Marx BP, Weathers FW, et al. Psychometric properties of the PTSD Checklist for Diagnostic and Statistical Manual of Mental Disorders-Fifth Edition (PCL-5) in veterans. Psychol Assess. 2016;28(11):1379–1391. PubMed CrossRef
- Picardi A, Pallagrosi M, Fonzi L, et al. Attachment in patients with bipolar and unipolar depression: a comparison with clinical and non-clinical controls. Clin Pract Epidemiol Ment Health. 2019;15:143–152. PubMed CrossRef
- Khan AJ, Bradley E, O’Donovan A, et al. Psilocybin for trauma-related disorders. In: Barrett FS, Preller KH, eds. Disruptive Psychopharmacology. Springer International Publishing; 2022:319–332.
- McGowan NM, Rucker JJ, Yehuda R, et al. Investigating the safety and tolerability of single-dose psilocybin for post-traumatic stress disorder: a nonrandomized open-label clinical trial. J Psychopharmacol. 2025:2698811251362390.
- Anderson BT, Danforth A, Daroff PR, et al. Psilocybin-assisted group therapy for demoralized older long-term AIDS survivor men: an open-label safety and feasibility pilot study. EClinicalMedicine. 2020;27:100538. PubMed CrossRef
- Watts BV, Schnurr PP, Mayo L, et al. Meta-analysis of the efficacy of treatments for posttraumatic stress disorder. J Clin Psychiatry. 2013;74(6):e541–e550. PubMed CrossRef
- Taylor P, Rietzschel J, Danquah A, et al. Changes in attachment representations during psychological therapy. Psychother Res. 2015;25(2):222–238. PubMed CrossRef
- Szigeti B, Weiss B, Rosas FE, et al. Assessing expectancy and suggestibility in a trial of escitalopram v. psilocybin for depression. Psychol Med. 2024:1–8. CrossRef
- Melhuish Beaupre LM, Tiwari AK, Gonçalves VF, et al. Antidepressant-associated mania in bipolar disorder: a review and meta-analysis of potential clinical and genetic risk factors. J Clin Psychopharmacol. 2020;40(2):180–185. PubMed CrossRef
- Goodwin GM, Croal M, Feifel D, et al. Psilocybin for treatment resistant depression in patients taking a concomitant SSRI medication. Neuropsychopharmacology. 2023;48(10):1492–1499. PubMed CrossRef
- Haft SL, Downey AE, Raymond-Flesch M, et al. A systematic review of participant diversity in psychedelic-assisted psychotherapy trials. Psychiatry Res. 2025;345:116359. PubMed CrossRef
Please sign in or purchase this PDF for $40.




